Clinical Scenario:
A 10-year-old boy with a history of bronchial asthma is brought to the emergency department with severe respiratory distress despite receiving three consecutive nebulizations of salbutamol and ipratropium bromide, intravenous hydrocortisone, and supplemental oxygen over the past hour. He is drowsy and able to speak only single words. Examination reveals a respiratory rate of 12/min (despite ongoing severe distress), marked use of accessory muscles, minimal bilateral air entry (“silent chest”), and oxygen saturation of 86% despite high-flow oxygen. Arterial blood gas analysis shows: pH 7.21, PaCO₂ 68 mmHg, PaO₂ 58 mmHg.
What is the most appropriate next step in management?
A. Intravenous aminophylline infusion
B. Intravenous magnesium sulfate
C. Non-invasive ventilation
D. Repeat nebulized salbutamol every 20 minutes
E. Tracheal intubation and mechanical ventilation
Correct Answer & Explanation
Correct Answer: E. Tracheal intubation and mechanical ventilation
Explanation: Management of Acute Severe Asthma
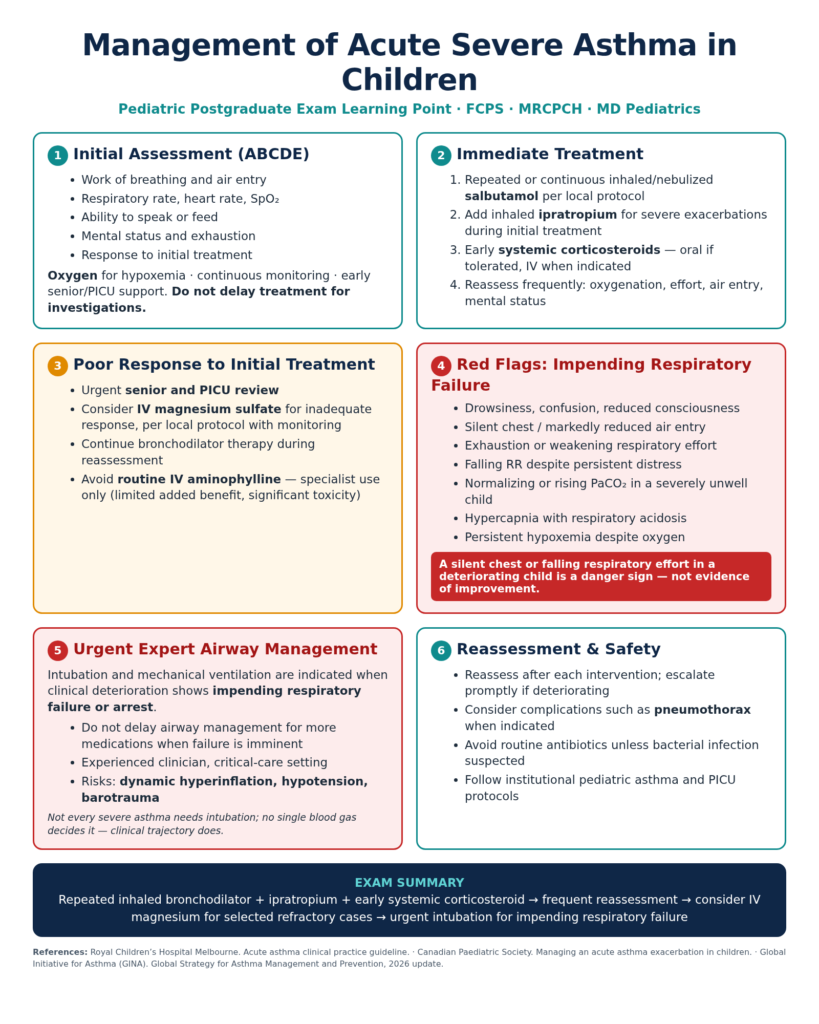
This child has life-threatening acute severe asthma with impending respiratory failure. The combination of altered consciousness, a silent chest, a falling respiratory rate, persistent hypoxemia, and hypercapnic respiratory acidosis indicates that effective ventilation is failing despite initial treatment.
Key clinical findings include:
Drowsiness: Altered consciousness is a danger sign and may reflect hypoxemia, hypercapnia, or both.
Silent chest: Minimal or absent air entry in a child with severe respiratory distress suggests critically reduced airflow. It is not evidence that bronchospasm has resolved.
Respiratory rate of 12/min: This is the key examination trap. A child with severe asthma is usually tachypneic initially. A falling respiratory rate accompanied by drowsiness and poor air entry suggests respiratory muscle fatigue and impending respiratory arrest, rather than improvement.
Persistent hypoxemia: Low oxygenation despite supplemental oxygen indicates severe disease and inadequate response to treatment.
PaCO₂ of 68 mmHg with pH 7.21: This confirms hypercapnic respiratory acidosis. Children with acute severe asthma commonly hyperventilate initially, producing a low PaCO₂. A normalizing or rising PaCO₂ in a child who remains severely distressed is concerning for inadequate alveolar ventilation and respiratory muscle exhaustion.
The child has deteriorated despite repeated inhaled bronchodilators, systemic corticosteroids, and oxygen. In this setting, urgent tracheal intubation and mechanical ventilation are indicated. Airway management should be undertaken by an experienced clinician in an intensive care environment because intubation and positive-pressure ventilation in severe asthma carry substantial risks, including hypotension, air trapping, and barotrauma.
Why the other options are incorrect
A. IV aminophylline infusion
Intravenous aminophylline is not routinely recommended for acute severe asthma because evidence of additional benefit is limited and toxicity can be serious, including arrhythmias and seizures. It must not delay definitive airway management in a child with impending respiratory failure.
B. IV magnesium sulfate
Intravenous magnesium sulfate may be considered for severe asthma that responds inadequately to initial inhaled bronchodilators and systemic corticosteroids. It may be administered as an adjunct while preparations for intubation proceed, provided this does not delay airway management. It is not a substitute for ventilation when respiratory failure is imminent.
C. Non-invasive ventilation
Evidence for non-invasive ventilation in children with acute severe asthma remains limited. It may be considered in carefully selected patients under close specialist supervision. However, drowsiness, an ineffective respiratory effort, and impending respiratory arrest make it inappropriate to rely on non-invasive ventilation in this case because airway protection and effective ventilation may be compromised.
D. Repeat nebulized salbutamol every 20 minutes
Inhaled salbutamol remains a cornerstone of acute asthma treatment, and bronchodilator therapy may continue during resuscitation. However, repeating nebulization alone is inadequate when the child has altered consciousness, markedly reduced air entry, and established hypercapnic respiratory acidosis with clinical deterioration.
E. Tracheal intubation and mechanical ventilation — Correct
The child has clinical features of impending respiratory arrest and inadequate ventilation. Urgent tracheal intubation and mechanical ventilation are the priority, alongside continued appropriate asthma treatment and intensive monitoring.
Learning Point
Recognize impending respiratory failure in acute severe asthma when a child develops:
Altered mental status, agitation, or drowsiness.
A silent chest or markedly reduced air entry.
A falling respiratory rate or weakening respiratory effort despite ongoing distress.
A normalizing or rising PaCO₂, particularly with respiratory acidosis.
Persistent hypoxemia despite oxygen therapy.
Examination pearl: In a child with severe asthma, a falling respiratory rate is reassuring only if the overall clinical condition is improving. If consciousness, air entry, or respiratory effort is deteriorating, suspect exhaustion and impending respiratory arrest. Do not delay intubation while trying additional medications that cannot correct failing ventilation.
Find high yield board review system wise pediatric MCQs
External Resources
Royal Children’s Hospital Melbourne — Acute Asthma Clinical Practice Guideline — pediatric assessment of life-threatening asthma, silent chest, and escalation of care.
Canadian Paediatric Society — Managing an Acute Asthma Exacerbation in Children — evidence-based treatment, IV magnesium sulfate, aminophylline, and indications for intubation.
Global Initiative for Asthma (GINA) — 2026 Strategy Report — international asthma management recommendations.
References
1. Trottier ED, Chan K, Allain D, Chauvin-Kimoff L. Managing an acute asthma exacerbation in children. Paediatr Child Health. 2021;26(7):438–439. Available from: Canadian Paediatric Society.
2. Royal Children’s Hospital Melbourne. Clinical practice guideline: acute asthma. Melbourne: The Royal Children’s Hospital; updated guideline available online.
3. Global Initiative for Asthma. Global strategy for asthma management and prevention: 2026 update. GINA; 2026.