Clinical Scenario:
A 2-month-old previously healthy infant is brought to the emergency department with poor feeding and irritability for 6 hours. On examination: the infant is pale, HR 280/min and regular, RR 60/min, capillary refill time 3 seconds, and BP is difficult to record. Peripheral pulses are weak. ECG shows a narrow QRS complex tachycardia with no visible P waves. The infant is alert but lethargic, with no IV access established yet.
What is the most appropriate immediate management?
A. Adenosine
B. Amiodarone
C. Cardioversion
D. Ice application
E. Vagal maneuvers
Correct answer & Explanation:
Correct answer: C. Cardioversion
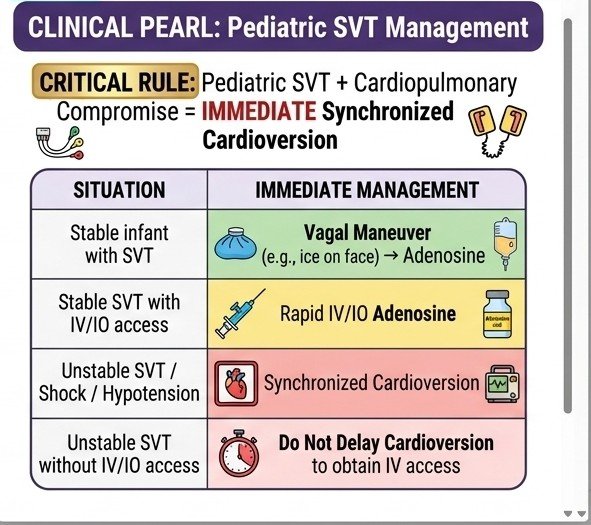
This infant has acute supraventricular tachycardia (SVT) with cardiopulmonary compromise, so the immediate treatment is synchronized electrical cardioversion.
Why this is SVT
Several features strongly favor SVT rather than sinus tachycardia:
- Heart rate 280/min — an infant heart rate ≥220/min strongly suggests SVT.
- Very regular rhythm.
- Narrow QRS complexes — consistent with a supraventricular origin.
- No visible P waves — typical of re-entry SVT.
- Abrupt symptomatic presentation with poor feeding and irritability.
- There is evidence of hemodynamic compromise: weak pulses, difficult-to-record BP, prolonged capillary refill and lethargy.
The 2025 AHA/AAP Pediatric Advanced Life Support algorithm defines cardiopulmonary compromise in tachyarrhythmia by findings such as altered mental status, signs of shock, or hypotension.
Why cardioversion is the best immediate treatment
The key discriminator in this question is hemodynamic instability.
Although adenosine is an important treatment for pediatric SVT, this infant has no IV access yet and is showing signs of shock. Therefore, treatment should not be delayed while attempting IV access or administering a drug.
For an infant with SVT and cardiopulmonary compromise, the current AHA/AAP PALS recommendations support synchronized cardioversion, starting at 0.5–1 J/kg. If unsuccessful, the energy can be increased to 2 J/kg. Sedation may be considered if appropriate, but cardioversion should not be delayed because of sedation in a compromised patient.
In this particular stem, the absence of IV access is an additional clue toward cardioversion.
Why the other options are incorrect
A. Adenosine — Incorrect
Adenosine is the preferred drug for acute termination of stable re-entry SVT when IV/IO access is available. The usual initial dose is 0.1 mg/kg rapid IV/IO push, followed by a flush; a second dose of 0.2 mg/kg can be considered if necessary.
However, this infant is unstable and has no IV access. Trying to establish IV access and give adenosine should not delay definitive treatment.
B. Amiodarone — Incorrect
Amiodarone is not first-line treatment for an unstable infant with narrow-complex SVT. Antiarrhythmic drugs such as amiodarone are considered only in selected situations, particularly when SVT remains refractory to appropriate initial management and with expert consultation.
D. Ice application — Incorrect
Ice/cold stimulation of the face is a vagal maneuver that can terminate SVT in some infants. However, vagal maneuvers are appropriate primarily when the child is hemodynamically stable. They should not delay cardioversion in an infant with shock or hypotension.
E. Vagal maneuvers — Incorrect
Vagal stimulation is recommended initially for SVT without cardiopulmonary compromise. In this case, the infant has weak pulses, poor perfusion, difficult-to-record blood pressure and lethargy. Therefore, synchronized cardioversion is indicated rather than attempting vagal maneuvers first.
Reference
American Heart Association & American Academy of Pediatrics. Pediatric Advanced Life Support (PALS), 2025 Guidelines — Pediatric Tachyarrhythmia With a Pulse.
Do you want to practice more MCQs on cardiovascular system ?