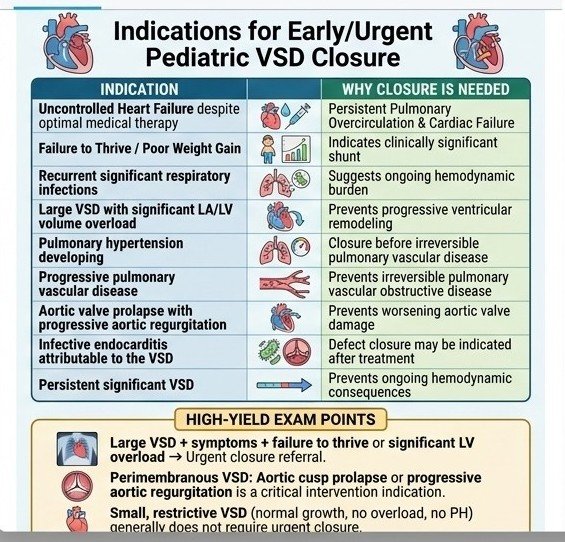
Clinical Scenario:
A 3-year-old girl presents with recurrent chest infections and poor weight gain since infancy. She was diagnosed with a moderate-sized perimembranous VSD at 6 months of age and has been on regular follow-up without surgical intervention, as she remained asymptomatic until recently. On examination: weight is at the 10th centile, RR 32/min, grade 3/6 pansystolic murmur at the left lower sternal border, and no cyanosis or clubbing. Echocardiography shows the VSD size unchanged at 6 mm, mild LA/LV dilatation, and normal PA pressure. She has now had her third episode of lower respiratory tract infection in the past 6 months.
What is the most appropriate next step in management?
A. Add ACE inhibitors and reassess in 3 months
B. Continue observation as the defect is small
C. Perform cardiac catheterization for shunt quantification
D. Refer for elective surgical closure
E. Start prophylactic antibiotics for recurrent infections
Correct answer & Explanation:
Correct answer: D. Refer for elective surgical closure
This child has a hemodynamically significant perimembranous VSD with evidence of ongoing pulmonary overcirculation and clinical impact, despite the absence of pulmonary hypertension.
Explanation
The important change is that the child, previously relatively asymptomatic, has developed recurrent lower respiratory tract infections and poor weight gain. These findings suggest that the VSD is producing clinically significant left-to-right shunting.
Although the defect is only 6 mm, management is not determined by diameter alone. The important factors are:
- Recurrent respiratory infections
- Poor weight gain
- Mild left atrial and left ventricular dilatation, indicating increased pulmonary venous return and LV volume loading
- Persistent significant VSD at 3 years of age
- Normal pulmonary artery pressure, meaning there is still an opportunity to close the defect before irreversible pulmonary vascular disease develops
In a child with a persistent significant VSD producing symptoms or significant LV volume overload despite medical management, closure should be considered. For a perimembranous VSD, surgical closure is commonly used when intervention is indicated.
Why the other options are incorrect
A. Add ACE inhibitors and reassess in 3 months — Incorrect
ACE inhibitors such as captopril may be useful for symptomatic heart failure due to significant left-to-right shunting, particularly in infancy while awaiting spontaneous closure or definitive intervention. However, this child is already 3 years old with persistent clinical consequences and LV volume loading. Continuing medical therapy alone would unnecessarily delay definitive treatment.
B. Continue observation as the defect is small — Incorrect
The absolute size of the VSD should not be the sole determinant of management. A 6-mm VSD can still be hemodynamically important. Poor growth, recurrent respiratory infections and LA/LV dilatation indicate that this is not simply an insignificant small VSD.
C. Perform cardiac catheterization for shunt quantification — Incorrect
Routine cardiac catheterization is not required when echocardiography clearly demonstrates the VSD and its hemodynamic consequences and pulmonary artery pressure is normal. Catheterization is generally reserved for situations in which non-invasive assessment is inadequate or pulmonary vascular resistance needs clarification.
E. Start prophylactic antibiotics for recurrent infections — Incorrect
Recurrent respiratory infections in this setting are a consequence of pulmonary overcirculation, not an indication for long-term prophylactic antibiotics. The underlying hemodynamically significant VSD needs to be addressed.
Clinical pearl
Persistent VSD + poor growth/recurrent chest infections + LA/LV dilatation = consider definitive closure, even when the VSD is not large by diameter.
Reference
MSD Manual Professional Edition – Ventricular Septal Defect (Pediatrics)
You can also solve another MCQ on Ventricular septal defect.