Correct Answer: B. Continue dietary control lifelong
Explanation:
This child has classic phenylketonuria (PKU) due to phenylalanine hydroxylase (PAH) deficiency. PAH normally converts phenylalanine (Phe) → tyrosine. In classic PKU, deficient PAH activity causes phenylalanine to accumulate in the blood and tissues.
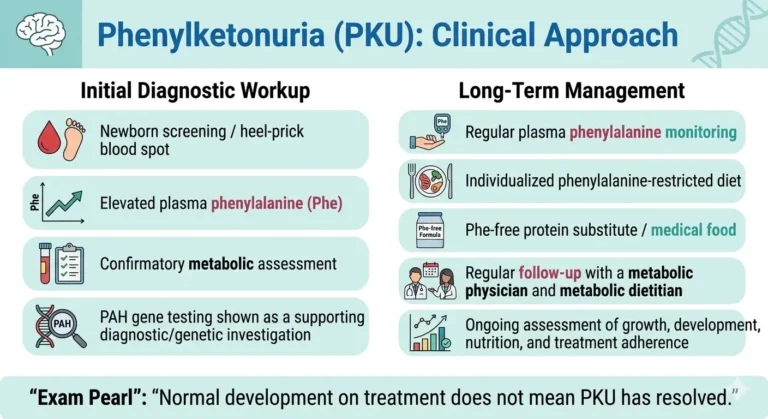
The key point in this question is that normal development and consistently normal plasma phenylalanine levels are the result of effective treatment—they are not evidence that the underlying metabolic disorder has resolved.
Current guidance recommends lifelong treatment for individuals with PAH deficiency whose untreated phenylalanine levels are above the treatment threshold. Treatment generally consists of an age-appropriate phenylalanine-restricted diet plus Phe-free protein/medical food, with pharmacologic therapy considered in appropriate patients.
Why must treatment continue?
Phenylalanine is an essential amino acid, so it cannot simply be eliminated from the diet. The objective is to provide enough phenylalanine for normal growth and protein synthesis while preventing excessive plasma Phe concentrations.
Persistently elevated phenylalanine can adversely affect the brain and is associated with neurocognitive and neurobehavioral problems. Importantly, the absence of symptoms in a successfully treated child does not mean that dietary treatment is no longer necessary.
Earlier approaches sometimes relaxed or stopped the diet during childhood, but evidence demonstrated that discontinuing treatment is unsafe. European PKU guidelines therefore recommend treatment throughout life because there is insufficient evidence that discontinuation is safe.
Why the other options are incorrect
A. Stop the diet at 2 years — Incorrect
There is no recommended age at which dietary treatment should routinely be stopped in classic PKU. Age 2 is sometimes relevant to the assessment of mild/benign hyperphenylalaninemia, but this is different from classic PKU.
C. Stop when IQ is normal — Incorrect
A normal IQ reflects successful early treatment; it does not indicate that the PAH deficiency has disappeared. The metabolic defect remains lifelong.
D. Restart only if symptoms develop — Incorrect
This is particularly dangerous because neurological and neurobehavioral consequences of elevated Phe may develop without an obvious early clinical warning. Treatment should be guided by regular plasma phenylalanine monitoring, not by waiting for symptoms.
E. Relax the diet after starting school — Incorrect
Starting school does not represent a metabolic milestone at which dietary treatment can safely be discontinued. Dietary Phe tolerance can be individualized and sometimes liberalized under metabolic-team supervision, but this is different from stopping treatment altogether.
 Exam Pearls
- Classic PKU = lifelong metabolic disorder.
- Early newborn screening + early treatment → prevents severe intellectual disability.
- A normal child on treatment does not mean PKU has resolved.
- Treatment aims to keep plasma Phe within the recommended target range.
- Never stop dietary treatment simply because the child is asymptomatic or has normal development.
- Dietary Phe intake can sometimes be carefully adjusted according to individual Phe tolerance, but this should be done with a metabolic physician/dietitian and continued biochemical monitoring.
- In classic PKU, medical foods provide Phe-free protein equivalents while natural protein/Phe intake is carefully controlled.
You can also practice another MCQ on metabolic disorder.
References
- Smith WE, Berry SA, Bloom K, et al. Phenylalanine hydroxylase deficiency diagnosis and management: A 2023 evidence-based clinical guideline of the American College of Medical Genetics and Genomics (ACMG). Genet Med. 2025;27(1):101289. doi:10.1016/j.gim.2024.101289.
- van Wegberg AMJ, MacDonald A, Ahring K, et al. The complete European guidelines on phenylketonuria: diagnosis and treatment. Lancet Diabetes Endocrinol. 2017;5(9):743-756. doi:10.1016/S2213-8587(16)30320-5.